Risk-Based MLR Review Triage for Branded Drug Content
MLR teams need triage logic to stop reviewing low-risk content like high-stakes claims.
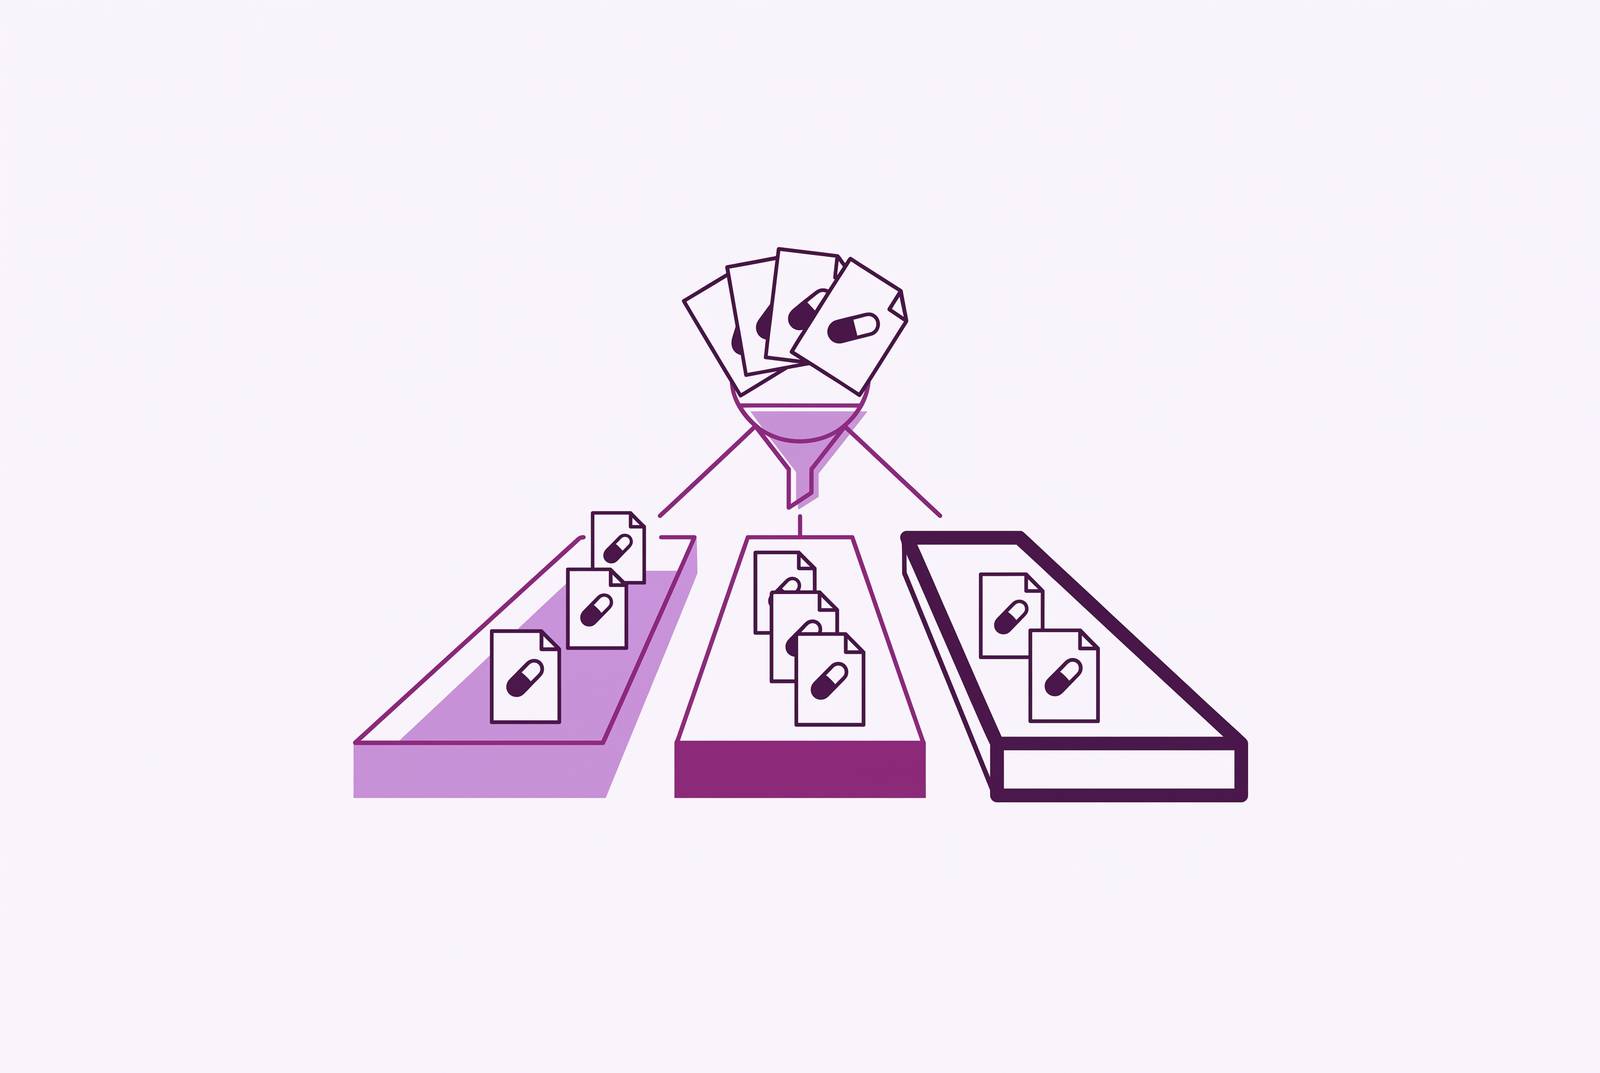
Content risk in pharma marketing isn't uniform, and MLR teams that review every asset with the same intensity are burning the resource they're shortest on: specialist time. A risk-based triage framework sorts content into tiers before it hits a reviewer's desk, so a dosing-reminder postcard doesn't sit in the same queue as a first-in-class oncology claim narrated by a celebrity spokesperson. Concentrate scrutiny where the stakes are actually high, and let the low-risk material move fast. That's the whole idea, and the rest of this piece is about what it takes to actually build it.
Medical, Legal, and Regulatory each check something different, and none of the three substitutes for the others. Medical checks whether clinical claims hold up against the evidence and match approved labeling. Legal looks at liability exposure, IP questions, and anything that reads like a comparative claim against a competitor's drug. Regulatory checks alignment against the rules that apply, which in the US means 21 CFR Part 202 for prescription drug advertising, among other frameworks. The scope is wide: sales aids, patient brochures, DTC broadcast spots, digital ads, social posts, congress booth materials, HCP portals. Every claim, every visual, every fine-print disclaimer runs through this gate before a physician or patient sees it, and that raises the practical question the rest of this piece is built around: given how much content now needs that gate, how do you decide what gets the full three-discipline treatment and what doesn't?
Why the enforcement environment makes a rigorous triage framework urgent right now
Start with scale. FDA issued more than 200 enforcement letters in 2025 for advertising and promotion violations, and 74 of those went specifically to pharmaceutical and biologic manufacturers. That split isn't background noise; it points to an active enforcement climate, and it's the reason triage stopped being a nice-to-have.
September 2025 made the point sharper. OPDP issued more than 100 letters, a mix of untitled and warning letters, in that single month alone, and whatever posture FDA held before, this is a more aggressive one now.
Here's the detail that should reorder everyone's priorities: FDA said outright that it used AI and tech-enabled surveillance tools to find non-compliant ads proactively. That changes the math on getting caught. A weak claim buried in a low-traffic banner ad used to have decent odds of going unnoticed; a tool scanning ad libraries at scale doesn't care how obscure the placement is.
What gets flagged most? A peer-reviewed analysis published in ncbi.nlm.nih.gov found omission of risk information is the single most common violation type, with unsubstantiated efficacy claims close behind. Neither of those is exotic or hard to catch, and they're exactly the kind of thing a properly staffed, properly sequenced MLR review is built to catch. So if the violations are this catchable, why do they keep happening? The next section gets into that.
The financial floor under all this isn't subtle. GSK settled for $3 billion in 2012 over off-label promotion, and Pfizer settled for $2.3 billion in 2009 on similar grounds. Across the industry, US life sciences companies paid roughly $9.8 billion in 2022 to settle False Claims Act and off-label promotion cases combined. The size of the penalty rarely tracks the size of the mistake. A single bad claim in a high-reach broadcast spot can trigger consequences that dwarf the cost of just reviewing the thing properly the first time.
And the ground underneath all of this is shifting for everyone at once. OPDP's Policy Division, the group that would normally issue clarifying guidance when the rules get ambiguous, was eliminated in April 2025, and it no longer exists. Going into 2026, teams have less advisory clarity to lean on, not more, right when enforcement is ramping up.
Where the current review process breaks down under volume pressure
Here's the mismatch nobody built the org chart for: review volume is growing three to four times faster than specialist review capacity. Medical, Legal, and Regulatory teams didn't get three to four times bigger; they got the same headcount and three to four times the inbox.
Some 83% of pharma companies report producing more content now than they were six months ago, and more than 65% of pharma marketers plan to grow their content budgets further. The pipeline isn't slowing down, and if anything, it's accelerating straight into that capacity wall.
Consider what "more content" means in practice. A single campaign can expand from 40 core assets into roughly 2,600 individual pieces once every channel adaptation, every audience variant, and every localized version gets counted. Every one of those, technically, requires review. Two thousand six hundred submissions from forty ideas isn't a rounding error in workload; it's an order-of-magnitude problem, and no amount of hiring closes that gap on its own.
Cycle times reflect it. At mid-sized and large companies, a review cycle commonly runs 50 to 60 days per piece, after pre-review prep, which itself can range anywhere from 5 to 150 days depending on the asset. Low-risk social posts average around 5 days, while high-risk broadcast ads in complicated therapeutic areas can run past 45 days. Treating a tweet-length reminder post like a Phase 3 oncology claim is where a lot of that spread comes from, and it's the clearest sign the current process has no sorting logic at all.
Here's the part that should make everyone in the review chain pause: 77% of approved content is rarely or never used by field teams. Most of what's chewing through review capacity right now never reaches a physician or a patient, and the bottleneck isn't just volume; it's volume spent on the wrong things. Incomplete reference packs, feedback scattered across three disciplines that never talk to each other, unclear versioning, and review steps run one after another instead of side by side all add days, and none of it adds safety.
So here's the position worth stating plainly: running a reminder postcard and a net-new efficacy claim through the identical review path isn't a compliance strategy. It's a capacity failure wearing a compliance costume, and pretending otherwise is the actual root cause behind most of the numbers above. Most teams treat this as a staffing problem, but it isn't. It's a sorting problem, and no amount of headcount fixes a queue with no triage logic at the front of it.
The four dimensions that actually determine how much risk a piece of content carries
Risk in this content isn't always intuitive, which is exactly why triage needs written criteria instead of a reviewer's gut feeling applied inconsistently from one review to the next. Four dimensions do most of the work, and treating them as equally weighted, which is what most checklists do by default, is the first mistake worth correcting. Novelty of claims should outrank the other three every time; it's the dimension that actually predicts enforcement exposure, and most checklists bury it under audience and channel questions that matter far less.
Novelty of claims sits at the top for that reason. A net-new efficacy or safety claim, one with no prior approval history, carries the highest risk in the whole framework, while a previously approved claim reused within documented guardrails carries far less. The question worth asking at intake is simple: is this claim showing up for the first time, or is it a governed reuse of something that already went through MLR once?
Audience matters, too, though less than most teams assume. DTC content answers to different regulatory requirements than HCP-directed material, and the review checklist has to reflect that difference rather than pretend one checklist fits both. Consumer audiences generally have less clinical literacy than physicians, which raises the bar for how clearly risk gets communicated in plain language.
Channel and format each carry a distinct risk profile. Broadcast TV answers to the CCN Final Rule's specific requirements. Social media introduces character-limit constraints that force claim restatement, plus the added variable of influencer involvement. HCP portals and field-team leave-behinds follow different norms for how data gets presented. The 2025 enforcement letters landed across TV, social media, virtual conference backgrounds, newsletters, sales aids, exhibit booths, print, sponsored links, online video, and webpages — a range of formats, each with its own distinct risk context, and none of them behave the same way.
Therapeutic area complexity is the fourth. Oncology, CNS, and cardiovascular treatments carry more nuanced adverse event profiles, more contested efficacy data, and historically more intensive FDA attention than, say, an anti-infective. The review checkpoints (dose information, adverse events, contraindications) need to flex with that complexity. A checklist built for a simple antibiotic just isn't built for a first-in-class oncology agent, and pretending otherwise is where gaps open up.
There's a fifth factor layered on top of all four: reach and spokesperson involvement. High-reach broadcast DTC sits at the very top of the risk hierarchy simply because of how many people see it. Here's a specific data point worth sitting with: nine of FDA's 2025 enforcement letters targeted promotion based on spokesperson or influencer activity. Most influencers and paid endorsers, reasonably, have no background in prescription drug advertising rules, and that training gap is now an actively enforced risk category, not a theoretical one.
These four dimensions don't sit in isolation; they compound. A novel efficacy claim, delivered by a celebrity spokesperson, in a DTC broadcast ad, checks every high-risk box at once, and that combination doesn't just deserve the most intensive review pathway available. It demands it, no exceptions and no fast-tracking regardless of deadline pressure.
How to translate those dimensions into a three-tier routing hierarchy
Building a hierarchy out of those four dimensions isn't about cutting corners anywhere. It's about putting the deepest scrutiny where it's earned and letting everything else move at a pace that matches its actual risk.
Tier 1 gets full multi-disciplinary review, no shortcuts. That means net-new efficacy or safety claims with no approval history. DTC broadcast ads governed by the CCN Final Rule, particularly Standard 1, which requires the major statement be presented in consumer-friendly language, and Standard 5, which bars audio or visual elements from interfering with how that risk information gets presented. It means spokesperson- or influencer-driven content, including media appearances and podcast placements. Launch and pre-launch materials for a newly approved indication. Anything in a high-scrutiny therapeutic area presenting data in a novel way. And any off-label adjacent communication, including SIUU materials, where FDA's January 2025 final guidance requires non-promotional, factual, neutral framing backed by peer-reviewed literature.
Tier 2 runs on an expedited or parallel track. Think channel adaptations of a campaign already approved elsewhere: a print DTC ad reformatted for digital display, or an HCP detail aid turned into an email. Think complex HCP data presentations where the underlying data already cleared MLR but the new format still needs regulatory and medical sign-off. Social posts where character limits force a claim to be restated more concisely carry real risk in that restatement, but not enough to warrant a full sequential review. Disease awareness content that never names the product but clearly implies it needs legal and regulatory eyes, though full medical review matters less there.
Tier 3 is the templated or automated pathway, and it's worth naming plainly: this is where most of the volume should live, if the modular architecture in the next section actually gets built. Modular reassemblies built entirely from pre-approved component blocks, where MLR only checks the new context and any genuinely new statements, not the underlying claim all over again. Translations and localizations with no substantive content changes need a compliance attestation from local regulatory rather than a fresh full review. Administrative, reminder-only material with no new claims at all. Safety-only content that just points back to the prescribing information within an already-governed template.
None of this works without discipline in how it's applied. The criteria for each tier need to be written down, shared across MLR and marketing operations, and used the same way every time. Otherwise individual judgment calls creep back in, and the whole point of building the hierarchy quietly evaporates.
Why modular content architecture is the structural prerequisite for triage to work
Here's the mechanism that actually makes Tier 3 possible; without it, the tier doesn't exist in any real sense. One approved efficacy claim, along with its supporting citation, its approved visual, its required risk language, and its allowed variants for HCP versus patient audiences, gets stored as a single governed block.
That block can then get assembled into a rep email, a banner ad, a section of a landing page, a congress leave-behind, a CRM nurture email. MLR reviews the new context each time and checks for any genuinely new statements, but it doesn't re-review the underlying claim over and over. One approved claim, many assets, one review: that ratio is the entire point, and it's the part most teams skip because it takes real work up front.
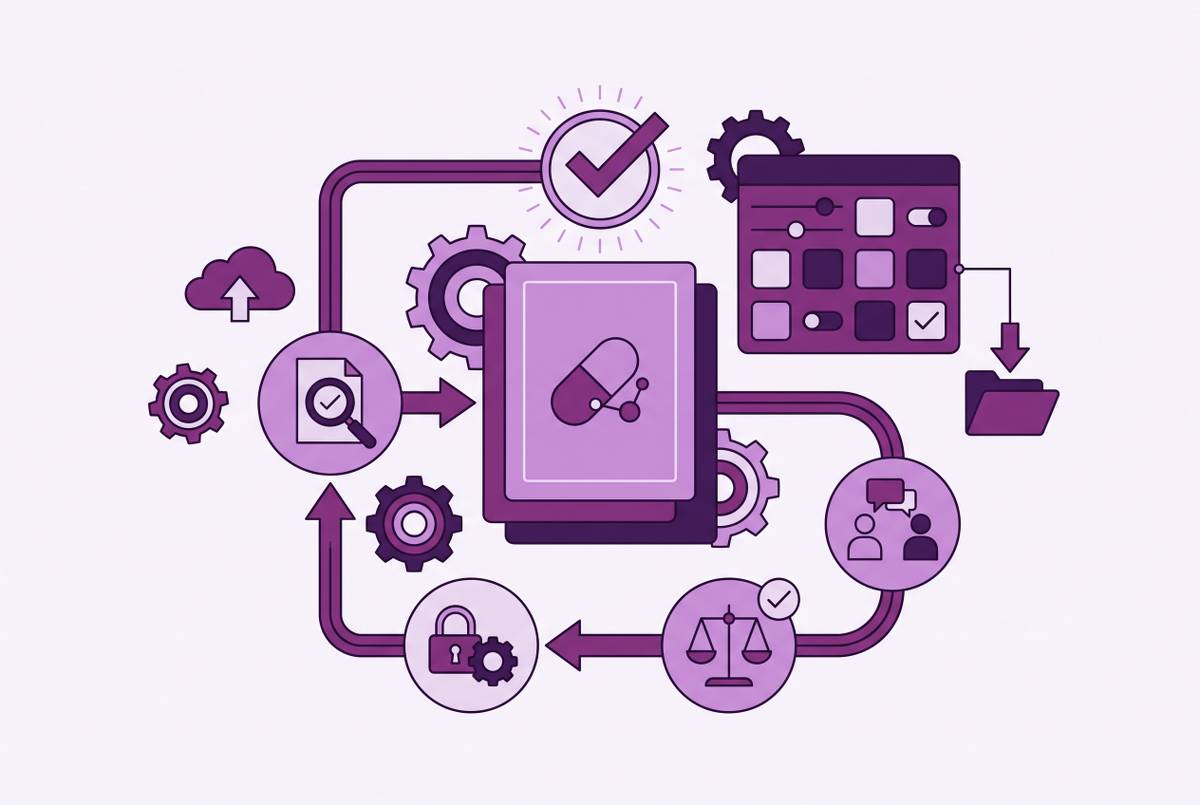
Making that work operationally takes actual infrastructure, not a shared drive with good intentions. Content has to be broken into discrete, version-controlled pieces: claims, references, safety statements, visuals, each tracked separately. Every module has to pass through full MLR before it enters the library, not after. Governance rules need to spell out exactly which combinations of modules are fine to assemble freely and which combinations trigger a fresh submission. And the content management system itself has to enforce that a module, once approved, can't be edited outside the governed workflow, not by a well-meaning designer trying to save time on a deadline.
Do the volume math and the payoff is obvious. That 2,600-piece campaign from earlier doesn't generate 2,600 full MLR submissions if the architecture is modular. Most of it flows through Tier 3 automatically, which frees up full-team bandwidth for the smaller slice of content actually introducing new risk.
Skip this infrastructure and the tiers exist only on paper. Content teams end up submitting full packages for everything anyway, because there's no reliable way to prove a given module hasn't been touched since its last approval. The triage framework and the modular library aren't two separate initiatives. One doesn't work without the other, full stop.
Where AI fits into a triage workflow and what it cannot do on its own
FDA used AI and automated surveillance to find non-compliant ads proactively in its 2025 enforcement wave. The same category of tool regulators point outward can be pointed inward, to catch problems before a letter ever gets drafted.
Inside a triage workflow, AI earns its place doing a handful of specific jobs well, and it should stay confined to exactly those jobs. It can pre-screen submissions for the most common violation patterns, omitted risk information, unsupported efficacy claims, before a human reviewer opens the file. It can check a submission against the approved modular library to confirm whether it's a genuine Tier 3 reassembly or whether it's quietly introducing something novel that belongs in Tier 1 or 2. It can flag CCN compliance issues directly in a DTC TV script, catching audio or visual elements that interfere with the major statement, or risk language that isn't written in consumer-friendly terms. And it can route submissions to the right tier automatically based on metadata alone: format, audience, therapeutic area, whether the claim is novel.
Here's what it should never be allowed to do: make the judgment calls that carry the actual liability. Any workflow that lets AI attempt that is building a problem, not solving one, and this is worth being blunt about. Medical judgment on whether a novel data presentation is scientifically sound and consistent with the current label isn't something a model can sign off on, and legal assessment of liability exposure in a comparative claim isn't either. Regulatory interpretation in genuinely ambiguous territory is arguably harder now than a year ago, given that OPDP's Policy Division, the group that used to issue clarifying guidance, no longer exists to weigh in.
The design principle that actually works treats AI as a compressor, not a decision-maker. It shrinks the time cost of Tier 2 and Tier 3 review, and it makes sure Tier 1 submissions land on a human reviewer's desk already pre-screened, so specialist time gets spent on real judgment calls instead of procedural checking. One caveat worth stating plainly: AI tools deployed without a defined triage framework behind them just generate more output that a human still has to sort by hand afterward. The speed is illusory without the routing logic underneath it.
How to build the triage framework into the workflow rather than alongside it
The single most common way triage frameworks fail isn't bad design. It's that the criteria get written down, filed somewhere, and then nobody looks at the document again at the moment it actually matters, which is submission time. The framework has to live inside the intake process itself, not next to it, and that's a systems problem, not a training problem.
Step one is a risk scoring intake form. Submitters answer four to six direct questions right at the start: is the claim novel, who's the audience, what channel, what therapeutic area, is a spokesperson involved, what's the estimated reach. Those answers map automatically to a tier, and the routing decision is visible to both marketing and MLR before review even begins, so nobody's guessing later about why something landed where it did.
Step two defines escalation explicitly, with no room for interpretation. Any change to what a claim actually means, not just how it's formatted, triggers automatic escalation to Tier 1 regardless of what the submitter selected on the intake form, and spokesperson or influencer involvement is a hard trigger, too, with no override available at intake, full stop.
Step three restructures how Tier 2 actually runs: parallel review instead of sequential. Medical, Legal, and Regulatory reviewing at the same time rather than passing a document down a chain can cut cycle time meaningfully without cutting the depth of any single discipline's input. European benchmarks put average review time around 20 days per asset with a mean of just 1.3 review cycles, and parallel structure is a big part of why those numbers hold up.
Step four keeps the modular library alive rather than letting it calcify. A module that hasn't been refreshed since the last labeling update is a quiet liability sitting in the system, so the library needs defined expiry dates and re-approval cycles built in. And given that 77% of approved content is rarely or never used by field teams, there's a real chance a large share of that library doesn't reflect what anyone actually needs anymore. Pruning it isn't housekeeping. It's risk management that happens to look boring.