Annotated Promotional Piece Requirements for MLR Submissions
Every claim in a drug ad must trace back to documented sources before FDA review.
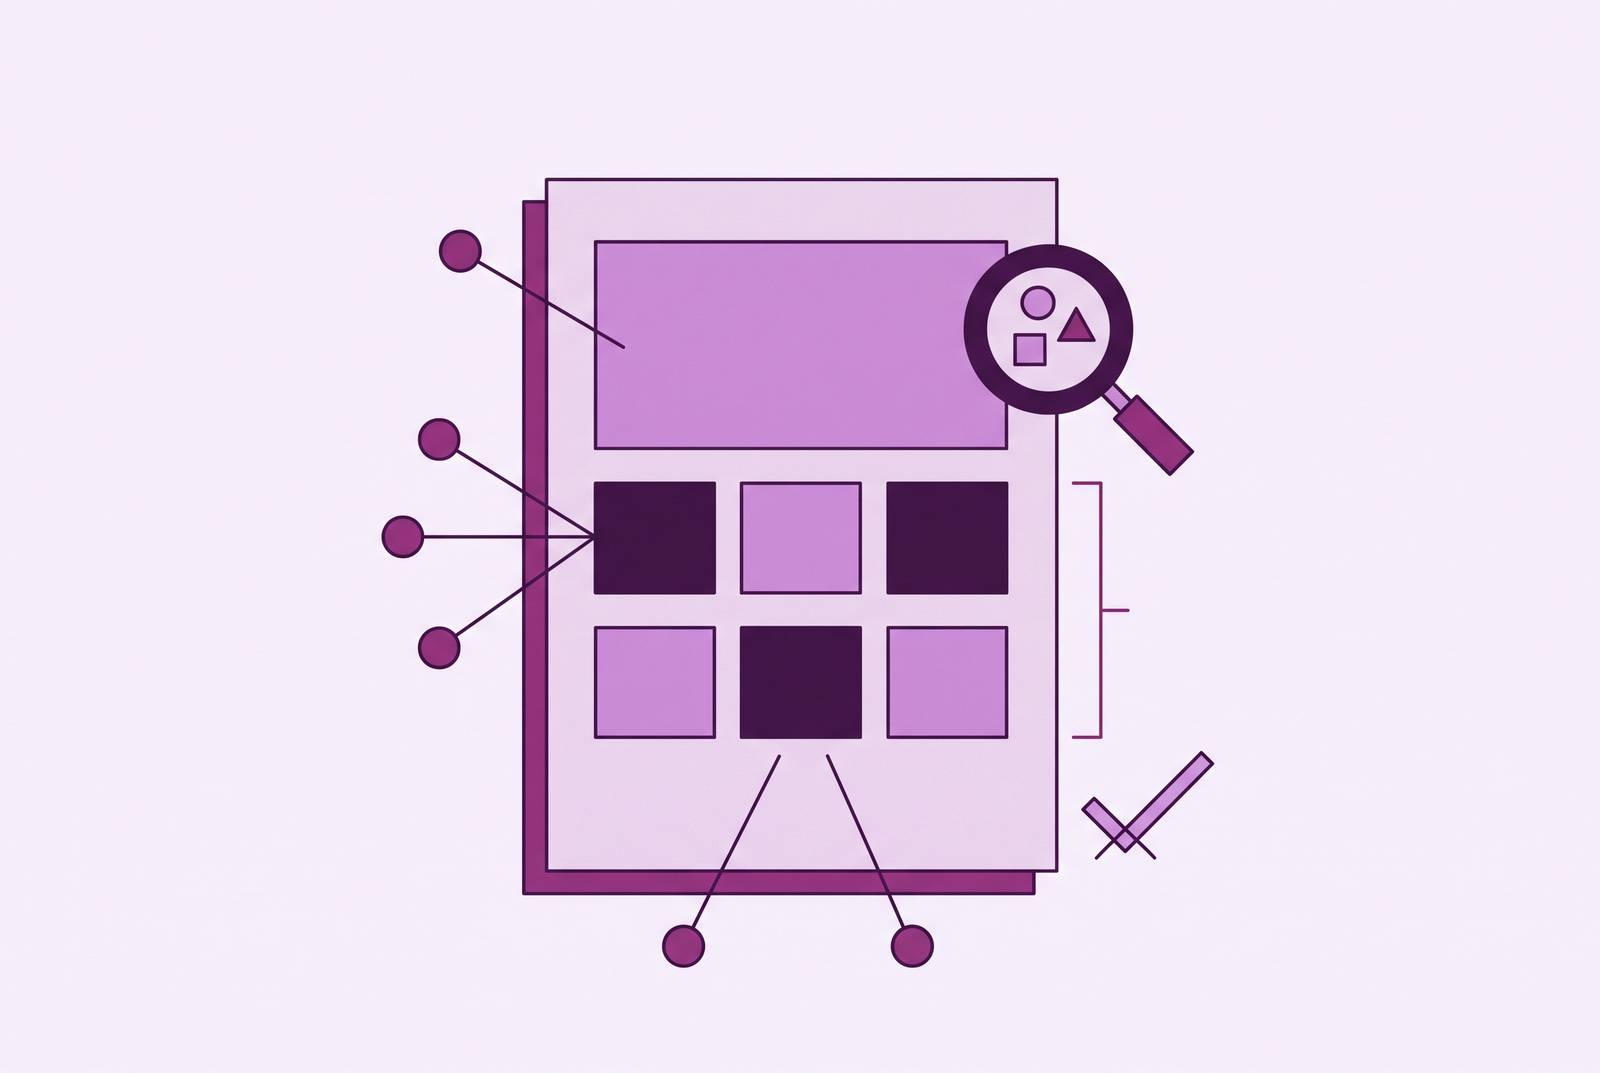
An annotated promotional piece is the paper trail that tells Medical, Legal, and Regulatory reviewers exactly where every claim in a drug ad came from. Skip that trail, and each reviewer starts hunting for sources on their own — a redundancy that shows up repeatedly in submission timelines, where reviews can stretch far beyond initial expectations. The rest of this piece walks through why annotation is mandatory, what it has to contain, and what happens when companies treat it as an afterthought. Working through the regulatory framework, the document layers, and the enforcement data, one pattern keeps surfacing: treating annotation as a submission formality rather than a drafting discipline is the single most common way companies waste six weeks they didn't have to lose.
The regulatory framework that makes annotation mandatory
Start with the law, since everything downstream traces back to it. The Federal Food, Drug, and Cosmetic Act, paired with Title 21 CFR Part 202, governs prescription drug advertising in the US. Two FDA offices sit on the receiving end of promotional submissions: OPDP, the Office of Prescription Drug Promotion inside CDER, handles drugs, while APLB, the Advertising and Promotional Labeling Branch inside CBER, handles biologics. Companies operating in Europe answer to a separate rulebook, Directive 2001/83/EC. Comparing the two regimes side by side, the logic underneath turns out to be the same on both sides of the Atlantic: show your work.
FDA's final guidance from June 24, 2019, titled Providing Regulatory Submissions in Electronic and Non-Electronic Format, Promotional Labeling and Advertising Materials for Human Prescription Drugs, spells out how to show that work. It finalized a draft that had been sitting since April 2015, and as of June 24, 2021, submissions falling under section 745A(a) must go in electronically, in eCTD format, using version 3.3 or later of the us-regional-backbone file. The mandate has limits, though. Voluntary advisory comment requests and responses to FDA information requests can still travel in non-eCTD formats — a distinction worth checking closely before someone spends a weekend converting files that never needed converting.
Every submission starts with Form FDA-2253, and it has to be the version dated 04-09-2021, filed at Section 1.1 of the eCTD structure. Post-marketing submissions run through 21 CFR 314.81(b)(3)(i) and 21 CFR 601.12(f)(4). Accelerated approval products carry their own wrinkle: firms under 21 CFR 314.550 and 601.45 that want to publish before FDA comments arrive have to notify OPDP or APLB through general correspondence first. Trace that requirement to its consequence, and it becomes clear why it matters: miss that step, and the annotation work downstream doesn't matter much, because the clock never even starts.
The four document layers every compliant submission must contain
Section 1.15.2.1 of the eCTD structure splits the submission into four distinct pieces, each doing a different job. Working through what each one actually verifies, the structure starts to look less like bureaucratic layering and more like four witnesses testifying to the same set of facts from four angles, none of them allowed to contradict the other three.
The first, 1.15.2.1.1, is the Clean Version: the piece exactly as it will land in front of doctors or patients, not a mockup or layout proof. A proof can ride along to show sizing or design choices, but the clean version is the baseline everything else gets checked against.
Second is 1.15.2.1.2, the Annotated Promotional Piece itself. FDA doesn't technically require this for post-marketing submissions, though it strongly encourages it, and for voluntary advisory comment submissions it's mandatory in practice, since the agency expects the source of every claim identified clearly. This is the layer the next section digs into.
Third, 1.15.2.1.3, is the Annotated Labeling Version: the approved Prescribing Information in both clean and annotated form, with annotations that cross-reference back to specific claims in the promotional piece. The Medication Guide rides along here too, where relevant.
Fourth, 1.15.2.1.4, covers Annotated References: everything backing a claim that isn't already in the PI. That splits into two buckets, references supporting efficacy or safety claims and references supporting disease-state or epidemiology information, and each has to point back to the exact claim it's propping up. One quirk worth flagging, and one that trips up teams running multiple campaigns at once: if a submission covers multiple promotional pieces, this whole four-layer structure repeats for each one. There's no shortcut for a company running five ads simultaneously, and nobody at FDA is going to offer one.
How to annotate the promotional piece itself: FDA's technical requirements
The rule at the center of this is simple to state and tedious to execute: every claim in the piece has to trace back to a source, and the annotated copy has to make that source obvious, not implied. FDA even published an annotated mock promotional piece as a working example, referenced in Section VI.F.3 of the OPDP Electronic Submission Guidance, so companies have a concrete template instead of guessing at format.
The mechanics matter here more than most teams expect. Annotations in the promotional piece link to specific entries in 1.15.2.1.3 or 1.15.2.1.4, and those links need to be hypertext links pointing to the exact page where the cited material lives, not the front page of a 40-page PDF. Consider what happens otherwise: a reviewer clicking a footnote and landing on a document's table of contents has not received a compliant annotation, and OPDP will not treat that gap kindly.
Digital and interactive pieces add a layer of complexity print ads never had to deal with. If the current approved file formats can't hold a fully functional interactive version, the submission has to show every interactive selection state as a still image with a note describing what it does. Work through an example: a dropdown menu with six options is, for annotation purposes, six separate claim surfaces, each one needing its own paper trail. Underneath all of it sits one baseline rule: claims lifted straight from the approved PI or the Important Safety Information count as pre-substantiated, but anything going beyond that language needs an external reference in 1.15.2.1.4, cross-referenced explicitly, since a claim without a PI citation gets no free pass.
What annotation looks like inside the internal MLR workflow before the FDA sees it
Before any of this reaches OPDP, it has to survive internal MLR review, and inside that process the annotated piece works less like a compliance form and more like the shared language Medical, Legal, and Regulatory use to talk to each other. Medical checks scientific integrity and risk-benefit balance, Legal checks litigation exposure and ad law, and Regulatory Affairs checks FDA alignment and submission mechanics. Three functions, one document, and annotation is what lets all three review the same claim without three separate meetings that all somehow run long.
Previously approved content gets annotated with its MLR-approved job number and, in most content management systems, linked directly to that approved record. The claim inherits its old substantiation, but only if the link is explicit; an assumption that "this ran last year, so it's fine" is exactly the kind of gap that turns up in a revision cycle three weeks later, usually on a Friday afternoon. New content gets flagged as new, no job number to lean on, and every claim needs its own reference unless it's pulled verbatim from the PI or ISI.
HCP and DTC materials get treated a bit differently, and here's where most teams underinvest. HCP pieces typically need references annotated and uploaded as separate reference material inside the client's system; DTC pieces still need substantiation, but the annotation formatting tends to be less granular. Underneath both sits a checklist that mirrors what FDA will eventually check anyway: key messages consistent with the approved label, consistency with Boxed Warnings and Contraindications and Warnings & Precautions and Adverse Events, prior review comments addressed and documented, a job code and version number visible on the material, and every hyperlink and footnote actually working, not just present.
Submission stage changes the depth expected. Concept, manuscript, and flat submissions each call for a different level of annotation completeness. Core launch advisory submissions carry an extra constraint worth underlining: claims can only draw on the PI, the pivotal or registration trial data, or publications directly tied to those trials, a narrow set of studies that actually anchor the label.
What OPDP is scrutinizing most closely in 2025 and 2026
The enforcement numbers from September 2025 make the stakes concrete: OPDP issued more than 100 enforcement letters, a mix of untitled and warning letters, in that single month alone. Analysis of FDA warning letters over time points to two violation categories showing up more than any others: omission of risk information, and unsubstantiated efficacy claims, in that order.
Both map directly onto annotation failures, once you follow the causal chain. A claim without a traceable reference is, by definition, unsubstantiated in the submission record; the underlying science can be airtight and it won't matter if the paper trail doesn't reach it. Missing risk information usually traces back to a broken cross-reference between the promotional piece and the annotated labeling version, the fair-balance connection that 1.15.2.1.3 exists to enforce in the first place.
Current OPDP focus, according to ProPharma Group's 2026 regulatory analysis, centers on Clear, Conspicuous, and Neutral presentation of risk, including dual-modality delivery where risk information shows up in both audio and on-screen text at once. Visual and audio balance is under the microscope too: imagery and animation can't distract from the major statement, meaning background music and visuals cannot overshadow the side-effect disclosures. Substantiation of magnitude-of-benefit claims, time-to-onset claims, and quality-of-life claims is drawing particular attention, since those are the claims most likely to oversell what the data actually shows.
Channel scope has widened well past broadcast DTC. Enforcement in 2025 reached HCP websites, corporate webpages, influencer content, earned media, and patient testimonials, and every one of those channels answers to the same annotation standard as a thirty-second TV spot, with nobody getting a pass just because the content lives on Instagram instead of prime-time cable. December 2025 brought finalized FDA guidance on promotional labeling for reference biologics, biosimilars, and interchangeable biosimilars, confirming annotation applies across media types and adding detail on how biosimilar-to-reference comparisons need to be handled.
The cost of getting annotation wrong
King & Spalding's year-in-review analysis puts total 2025 enforcement letters for prescription drug advertising and promotion above 200, with a surge concentrated in the final quarter, according to that same analysis. Weighed against the historical record, that figure marks a floor rather than a ceiling.
History supplies the ceiling. GlaxoSmithKline's 2012 settlement, at $3 billion, was at the time the largest healthcare fraud settlement in US history, centered on off-label promotion and a failure to report safety data to FDA. Pfizer's 2009 settlement came in at $2.3 billion for similar promotional violations. Set side by side, these two cases suggest something the letter counts alone don't: enforcement letters mark the floor of exposure; settlements like these are what happens when the underlying problem never gets fixed and just compounds year over year.
There's a quieter cost too, one that never makes a press release. MLR review cycles can stretch to 40 days, and the single biggest driver of that delay is content bouncing back through revision: claims without substantiation, incomplete fair balance, references that don't match the claims they're supposed to support. Tracing those three failure points back to their origin, all of them are exactly what complete annotation catches before the first review meeting even happens. Skipping annotation moves the delay downstream and hides it inside a revision cycle, where it becomes harder to trace back to the root cause. There's also a reputational angle sitting underneath all of it: enforcement letters are public documents, and a warning letter tells every prescriber, payer, and institutional partner reading it that a company's promotional practices didn't hold up under FDA review.
Building an annotation process that holds up across submission types and review cycles
Annotation quality is a process question before it's ever a document question, and this is the part most teams get backwards. Comparing teams that build the reference pack and the annotated copy before drafting the actual piece against those that retrofit sources onto finished copy, the pattern holds consistently: the former run fewer revision cycles. That ordering sounds almost too simple to matter, and yet it's the difference most often cited between smooth submissions and painful ones. Build the annotation first, then write the ad copy around what's already sourced, rather than reversing that sequence. Some content teams structure drafting around sourced claims for similar reasons.
That starts at the brief stage: every meaningful claim gets sorted into "comes from the PI or ISI" or "needs an external reference in 1.15.2.1.4" before a single line of copy gets written. Claims about magnitude of benefit, time to onset, or quality of life should get flagged early, since those face the sharpest scrutiny under current OPDP priorities.
Internal conventions matter more than they get credit for. A job code and version number belong on an asset from the first draft, not bolted on the week before submission. Previously approved content gets linked to its MLR job number explicitly; new content gets flagged as new, no exceptions, no grandfathering in a claim just because it looks familiar.
Digital and interactive assets deserve default treatment as annotation-heavy, with every interactive state mapped to its still-image representation well before submission prep begins, not the week it's due. For voluntary advisory comment submissions, treat the annotated copy as mandatory, because that's how FDA treats it regardless of what the letter of the guidance says. Keep core launch claims restricted to the PI, pivotal trial data, and directly related publications rather than every study that happens to mention the drug favorably.
One more habit worth building: track unresolved comments from prior review cycles as a standing input into the next one. An old comment that never got addressed doesn't disappear; it resurfaces in the next submission, often right before a filing deadline. Tying claims to evidence at the drafting stage, instead of retrofitting annotation once the piece is "done," compresses review timelines and cuts the back-and-forth that makes MLR approval feel less like a checklist and more like a negotiation nobody agreed to have.