Core Claims Matrix Development for New Drug Approvals
Structured claims mapping helps pharma avoid regulatory trouble at launch.
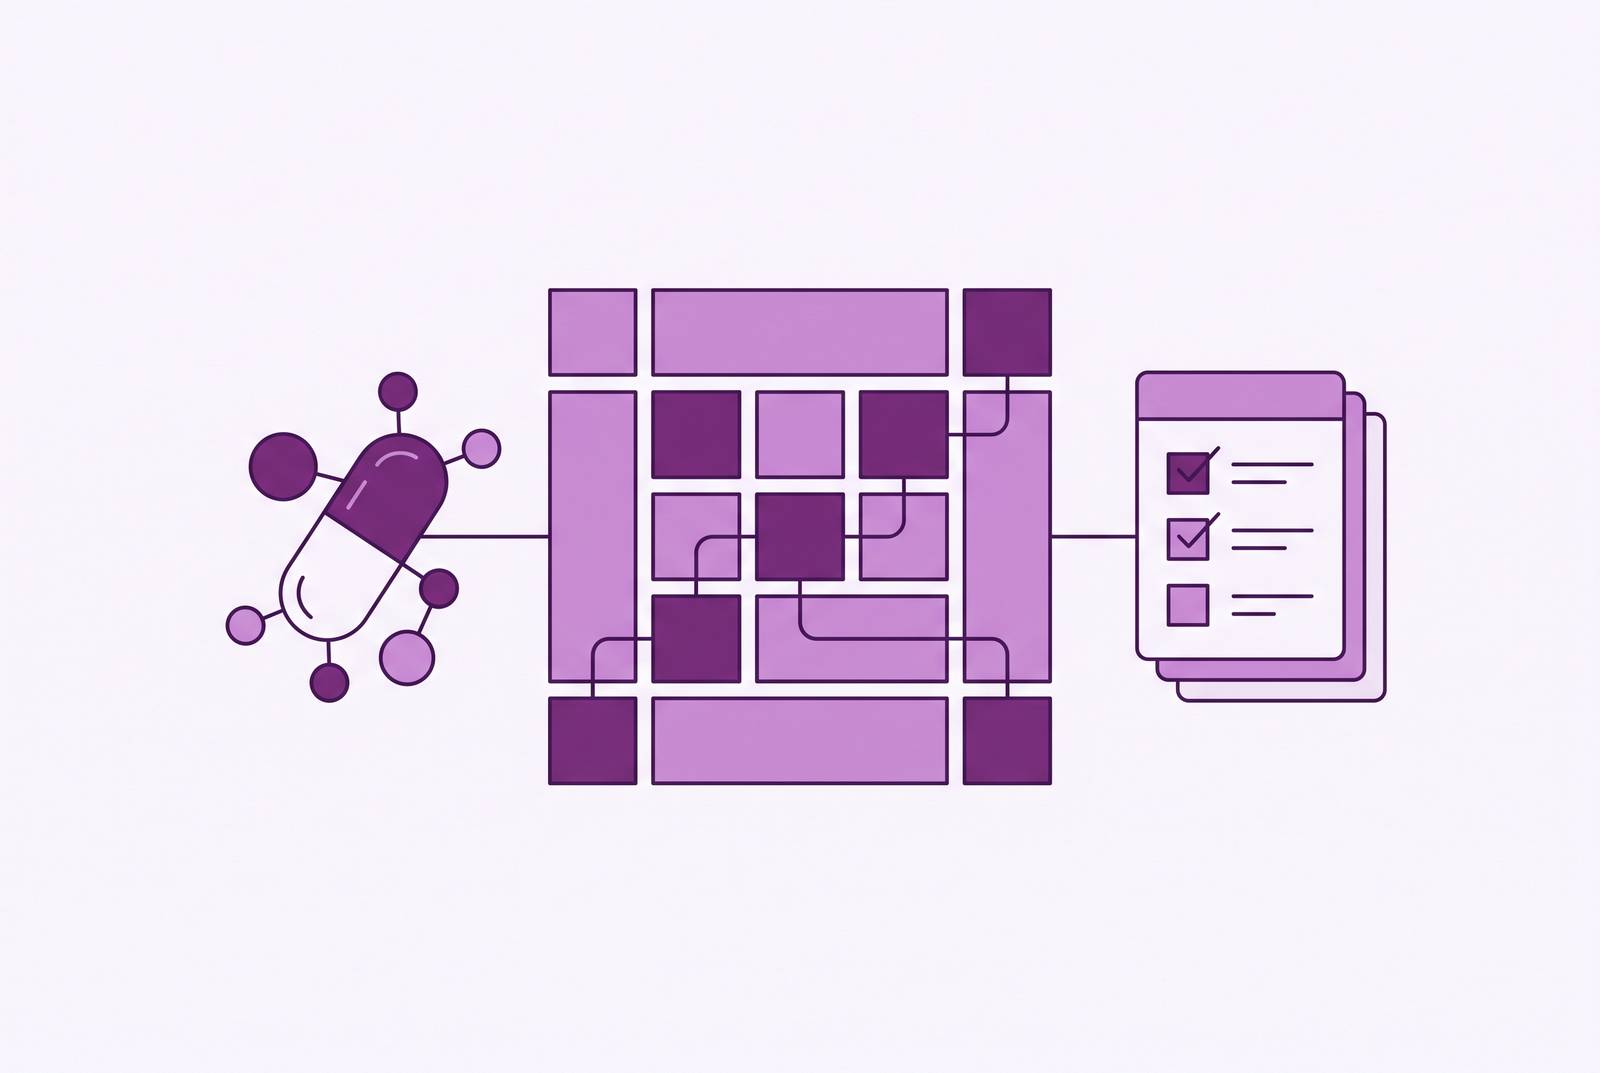
The core claims matrix takes the approved drug label and makes it practical: each allowed claim in one structured map, sorted for strength, backed by evidence, then cleared for chosen audiences and media channels. It isn't just paperwork. It's the difference between a launch that survives regulatory scrutiny and one that draws a warning letter three months after the PDUFA date.
In 2024, the FDA approved 50 drugs, near the 47-a-year mark from 2015. What that figure actually shows matters more: first-in-class molecules made up 48%, lacking any direct comparator; 52% treated rare conditions for few expert prescriber groups, and 33 used an expedited pathway. Once a medicine clears Priority Review, the six-month timeline means claims preparation must begin long before the FDA's approval letter shows up. These factors keep development complicated. It makes claims work after launch much harder than it seems.
Reading the label as a claims source, extracting what can actually be said
A marketing claim may only point to one legal source: the approved label, or prescribing. Regulatory and clinical needs shape it, so converting that into plain language comes first.
Every label section tells you a new thing. Indications and Usage holds the approved indication wording, which is the most defensible claim across the entire matrix but often narrower than marketing groups prefer. Clinical Studies holds patient population data, efficacy endpoints, plus trial design used in every quantitative claim. Use that data in context and accurately, rather than picking whichever subgroup appeared strongest. The Warnings plus Precautions section, along with Adverse Reactions, include required risk language with every claim, while this pairing isn't optional or trimmed unless Medical, Legal, or Regulatory (MLR) gives sign-off. Clinical Pharmacology holds mechanism-of-action language, usually workable in HCP materials, frequently off-limits to a lay audience unless it's restated simply.
The main rule is easy to explain but tough to enforce: copy that label exactly, then check if your paraphrase works. When any paraphrase changes the point, even a little, it is a leading cause of a FDA compliance letter. The Office of Prescription Drug Promotion received over 70,000 Form FDA 2253 submissions in 2024, and omitting required risk language can trigger compliance issues. Miss the extraction, and that's where the risk slips through.
TIDES compounds and Biologics, including oligonucleotides plus peptides, took a bigger share of 2024 approvals and need extra attention here. How these drugs work involves several processes in the body, and promotional text often flattened them into a single line. And for drugs on an expedited pathway, the label may carry surrogate-endpoint language, "demonstrated improvement in [biomarker]," rather than confirmed clinical outcome data. Your matrix needs to flag such claims as conditional right away, before any reviewer catches what post-market studies still need to prove.
This step produces a working annotated transcript, with each claimable bit on the label tagged by source section. All later stages are built on this transcript alone.
Organizing extracted claims into a tiered structure by evidential strength and strategic weight
Because a label claim carries varying weight, our matrix needs showing that hierarchy openly instead of leaving it implicit.
One workable approach uses 3 tiers. Core claims make up Tier 1. They cover the key endpoint for efficacy, the language for the approved indication, plus risk overview. You'll find them in almost each asset, holding the entire story together. Tier 2 covers backup claims: quality-of-life measures, subgroup data, non-primary endpoints, brought in to build up value dossiers and HCP materials. Tier 3 covers contextual claims plus fresh ones: mechanism detail, post-hoc analyses, real-world evidence taking shape, applied sparingly with tighter audience rules and tighter channel rules.
Strategic weight and evidential strength aren't the same thing, and the usual error here is seeing them as one. In rare-disease launch planning, evidence from the Tier 2 subgroup may count commercially above the Tier 1 endpoint when that subgroup makes up the real patient population. In 2024, Twenty-six approvals held Orphan Drug Designation; there, each tier's audience is unusually well-informed yet tiny, so what amount of detail fits each one shifts.
First-in-class drugs, nearly half of last year's approvals, usually launch without a direct comparator. Flagging that gap, the matrix needs to stop anyone implying a comparative edge the data can't back. Without head-to-head data, Mechanism-of-action language often bears strategic weight, and ignoring that gap means any claim risks overstating the trial's real findings.
Here, every row carries 5 items. They are the claim wording, the label's source section, what tier it sits at, the evidential category (exploratory, real-world evidence, or otherwise), and a flag for strategic priority. The tiering picks stay open for now. They get checked and revised during cross-functional review rather than finalized by marketing.
Mapping each claim to its substantiation package before any asset is written
Every claim in the matrix has to answer one question on demand: if a regulator, a payer, or a plaintiff's attorney asks what supports this, can the team produce a full answer inside a day?
It's made up of four components. The source: the specific section and location within the approved label. For the clinical data source, use the study writeup, the printed trial, or internal records. The context: its design, the population, and the number itself, since each claim built from a 500-patient Phase 3 trial changes if its basis was some subgroup of 50 patients, even when that wording matches. Finally, the risk piece: what exact language must appear with that claim in every channel.
Payer-facing claims need something further beyond this. To get favorable formulary status, Insurers plus health plans want real-world evidence first. That means pharmacoeconomic work, quality-adjusted stats, adherence results, plus hospitalization-reduction numbers must have mapping done across every source. Claims data, health records, patient registries, and longitudinal studies all fall under official guidance. In 2024, FDA gave guidance for judging real-world data sources, including health records plus claims data, when they’re assessed under regulatory review, and that guidance outlines criteria for evaluating real-world data sources.
When the backing still needs work, flag it openly. A claim that's commercially attractive but not fully backed gets logged as "in development," with a named owner and a target date, rather than sitting quietly until an MLR reviewer flags it during a submission crunch. And since your substantiation map feeds right into that MLR submission packet, getting it ready early shortens the review cycles. Reviewers look over what's there rather than chasing down sources.
Defining the audience and channel permissions for each claim
Clinicians rarely react like those they treat. A clinician looks for trial, endpoint definitions, design, plus peer-reviewed background context. The patient asks how this drug shapes their routine, using language they parse without medical training. That one version for a claim often fails one of the two audiences, so this matrix needs its explicit audience field, not a guess that any clearance covers all.
Most of it fits into 4 groups. Clinical context is what HCP-only claims need to work: comparative data, mechanism detail, subgroup breakdowns. Once cleared, consumer-facing channels can carry Patient and DTC claims in simple language that includes the required risk details. For Payer plus HEOR claims, either pharmacoeconomic evidence or real-world evidence is used, then formatted into value dossiers plus formulary submissions. Unrestricted claims, mostly core indication language that's paired alongside required risk details, work in every channel.
Channel works with audience as a further factor: medical print, sales materials, online banners, patient pages, decks for talks, news statements, platform updates. Each medium carries its own risk-disclosure duties, and some just won't run particular claims. A 15-second TV ad has no room for all the risk information a biologic requires, so the constraint on its own rules against certain Tier 1 claims there, even if the data behind them is excellent.
These channels need extra care today. Regulatory scrutiny applies equally to AI-generated content shared across those channels and to copy a human writes. According to a Lewis report from April 2026, the FDA sent a warning letter to a medication company citing improper AI use. In 2026, payer messaging is being built at a finer granularity level than before: content tailoring now targets the population of each payer, their outcome aims, and their spending, so the matrix row for payers needs matching specificity, not one broad "managed care" category.
Once you finish, each row carries the claim and tier plus substantiation, allowed audiences and channels, with required risk accompaniment together.
Running the matrix through MLR review without letting it become a bottleneck
In MLR review, Medical, Legal, and the Regulatory perspectives converge around content to assess the science, legal risk, plus regulatory compliance. Put your matrix into review before building any asset, so each one comes from a spot that's cleared already.
Our workflow has five stages. Start by building a complete submission pack: each claim, the label source, the substantiation package, audience plus channel permissions allowed, plus its version number tied to that matrix. Next, sort by risk: core Core claims undergo full review, while exploratory claims may require additional scrutiny based on their evidential support. Next, carry out a review with named owners, with every reviewer annotating chosen rows instead of marking the file into an undifferentiated mass. Handle every note during one revision round, logging all exceptions plus escalation items out in the open so old fights won't resurface each time another asset gets built. Last, get sign-off on each claim, archive its approved version by day, and store records linking each matrix item to assets built from it.
That kind of review doesn't just happen once. When the label changes, a fresh trial readout or post-market study finding creates another matrix version, so your archive must let you reconstruct what version governed every asset on what date.
Veeva Vault PromoMats, built specifically for promotional pharmaceutical review, handles claim banks, MLR templates for workflow, multichannel approval status, alerts for expiration, and reporting that's audit-ready. It suits bigger groups juggling multi-country demands alongside their current Veeva environment.
The payoff you get from matrix-level reviewing: asset groups quit re-arguing a claim repeatedly whenever a deliverable appears. Once a claim is matrix-approved, it can be used in materials with an easier review, provided the rules for channel and audience are followed. A frequent mistake happens when teams handle the matrix review like some formality tacked onto materials already being built. And at that point, rewrites eat budget and the launch date is slipping. Groups that jump into making the asset and view their matrix like paperwork after afterward always wind up doing rewriting on the sales aid right before launch time.
Extending the matrix to cover AI-generated content and AI-surface visibility
Sick people and their physicians both use AI to look up drugs today, so this matrix must see it as a real channel rather than an afterthought. A Rock Health Consumer Adoption Survey found that 32% of US adults have used AI chatbots for health-related questions. HCPs often mix ChatGPT or Perplexity with specialty medical systems when making a single clinical judgment, with no clear boundary between them.
AI-generated overviews appear for many informational searches, including health-related queries. An AI's take on any newly approved drug amounts to a claim, even if marketing never touched it.
Once Content clears MLR review, AI tools still might not cite it, so naming this gap matters. Medical-legal review usually drops the level of detail AI tools require to reference correctly, and any hedged language passes by unnoticed. Even after approval, data lags by many weeks or more, meaning any drug that got approved during 2025 might not appear accurately in responses from AI until deep inside 2026 or later.
This matrix helps bridge the gap. From approval forward, place claims that are citation-ready into sources that are high-authority and AI-retrievable, and this matrix defines which claims get cleared for use and the wording to use. Because AI tools pick sources reinforced inside clinical registries, databases for medical research, plus peer-reviewed papers carrying heavy citation counts instead of just brand-owned sites, our matrix must flag every Tier 1 along with Tier 2 claim that needs to show up in those external places specifically.
Company scale won't tell you AI citation share; thinking it will needs correcting now. Some pharmaceutical companies achieve high citation rates in AI responses by ensuring their data appears in authoritative external sources. Any newly approved drug begins from nothing unless visibility is built deliberately, one row at a time, just as the label was put into plain words originally.
Regulatory risk sticks with content everywhere. During September 2025 the FDA issued many warning notes for misleading marketing, and an April 2026 letter citing improper AI practices shows that keeping approved claim language plus audience rules covers AI-generated content just like a paper sales aid. One concrete step: give every matrix row its own GEO/AI-surface entry recording if each claim is structured with AI extractability in mind, what external sources carry the seeded copies, and if checks have confirmed each AI-surface paraphrases it accurately. Some firms already monitor this with pharma teams, checking on hallucinated and outdated drug descriptions, with reporting citation results against each matrix. Some platforms enable sponsored placements in large language models, making that oversight a regular habit rather than a one-off check.
Keeping the matrix current through post-approval label changes and data updates
A claims matrix built upon launch remains valid only while its label goes unchanged, and for typical drugs that stretch is short. Each time a supplemental regulatory request grows the indication, brings in another patient population, or changes the risk section, it resets what the claims matrix can state. Post-market study data for a drug with accelerated-approval can turn early language using surrogate-endpoint into outcome claims now confirmed, or, when tougher, lead to removing a claim that no more holds up.
Every one of these triggers must generate its own dated matrix version, not silently revise the one already in place. Any version number within an MLR pack for submission needs to match the label backing that claim, so staff can check an asset built months ago against what governed it then and justify it even after several changes shift those goalposts.
The current regulatory backdrop means you can't assume things will stay the same. CBER approved only 9 BLAs during 2025, well below the 22 of 2023 and the 24 of 2024, and with FDA staffing shifting, nobody knows how soon guidance will come out after this. That backdrop doesn't alter the core principle: a label granted with approval stands as legal documentation, not a static marketing asset, and it can shift. Any matrix not built for fast re-versioned changes will in time authorize one claim that its label can’t back. At that point, you're dealing with compliance rather than routine work.